The Challenge of Critical Thinking in EMS

This article first appeared in “Ambulance Today UK” – August 2019 edition

We will be exploring the advantages of being a critical thinking emergency medicine practitioner, and how it can positively benefit, us, our colleagues and our patients; and most importantly why we don’t really have an option, but to be critical thinkers.

 In Rosen’s Emergency Medicine, Chapman, et al, describes the critical thinking process as having three parts: medical inquiry (history, physical exam and diagnostic testing), clinical decision-making (a cognitive process that evaluates information to diagnose or manage a patient’s condition) and clinical reasoning, which involves both medical inquiry and clinical decision-making.

The challenge of the EMS educator/facilitator is how to instil those three concepts into the practitioner’s patient care approach, as the result will be a more focussed practitioner who has learnt the value of critical thinking and life-long learning. Critically Thinking is to be desired by EMS providers at every level, yet the concept isn’t easily defined, quantified or taught.

That’s because critical thinking only becomes real in practice; clinicians, critical and lateral thinkers are moulded in the field. Theory, guidelines, protocols, linear thinking is learnt in the classroom. That is not to downplay the importance of class time, as that is the foundation on which critical thinking rests. What follows on, is experience, continuing education, currency of competency and clinical mentoring. Learning that patient treatment plans fit into the continuum of clinical reasoning, as all patients are different. On the streets, patients don’t follow the script as per your last patient simulation. Thus, the gravity of responsibility you have, becomes intimidating.
Carl von Clausewitz, in his treatise “On War” wrote “Any complex activity, if it is to be carried on with any degree of virtuosity, calls for appropriate gifts of intellect and temperament.”

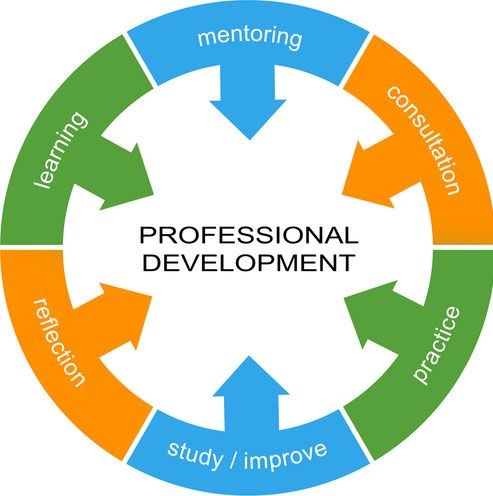
This doesn’t mean that everyone who learns something, immediately becomes an expert. For the lifelong learner, everyone has something of value to contribute, irrespective of what environment or years of experience are on the table. Part of lifelong learning is contributing to the pool of knowledge. Effective teaching, just like effective learning, begins with listening before talking. Lifelong learning is a commitment to taking moments out of each day, reflecting on the processes and patients, pushing to improve our knowledge, skills, patient care and attitudes.

Every patient contact is a clinical mystery waiting to be solved, by you the (detective) practitioner. They are relying on your educational experience, critical thinking, your knowledge that you integrate and update continuously – right down to that “interesting paper” you read last night! No patients are created equal, today’s cardiac patient will not match tomorrows, not all cardiac arrests are equal. Hence, we cannot rely on overly simplistic guidelines/protocols We need to critically analyse each patient, rhythm strip, against our font of knowledge and our vested clinical practice guidelines.

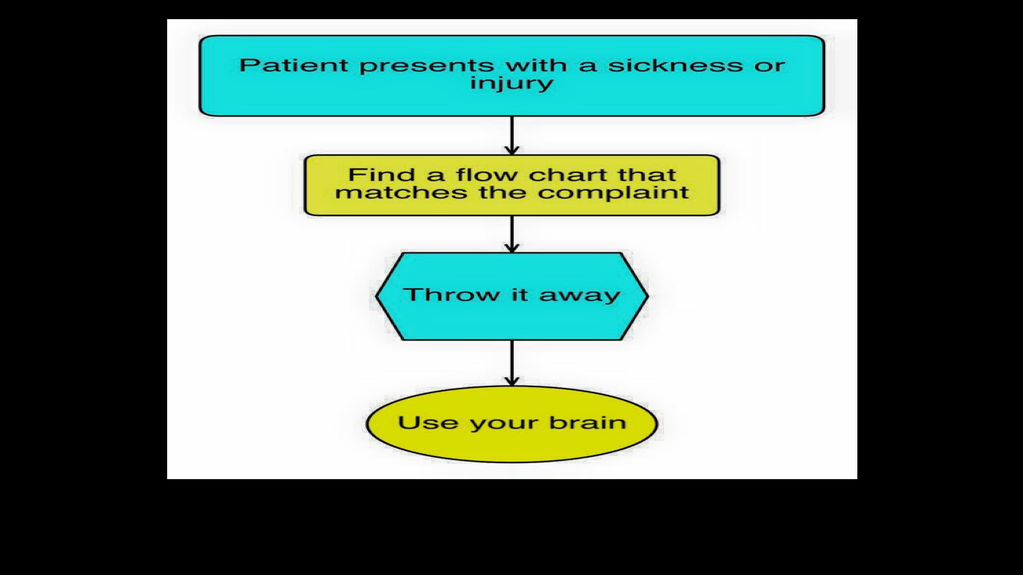
Critical thinking skills ask of us, to use our brain, and not blindly follow a pre-set protocol; evidence-based medicine keeps changing and – using one’s brain as opposed to blindly following a protocol would be short sighted and not always in the best interest of optimal patient outcomes. Seeking, questioning, evaluating, integrating and sharing every day, is an opportunity to get better at our passion (chosen profession), where patients rely on us for their lives. Knowledge and decision-making should be based on clinical findings on that case on that day, it’s not just a set of psychomotor skills and blindly followed protocols.
As a thoughtful science-based practitioner, learn to be iconoclastic, adopt a questioning, reflective approach to your practice. My mantra when looking at new and/or challenging concepts/modalities is as follows:

Is it evidence based, current, documented, cross referenced and is there a perceived bias (mine or the writers)?

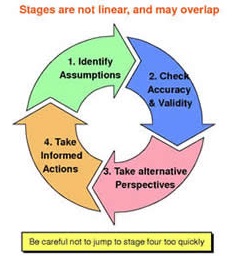
All pre-hospital emergency care practitioners should strive to be clinicians/critical thinkers, irrespective of their level of care, age or experience. Continuous lifelong learning ensures competence and confidence, allowing you to have the lateral thinking skills to break the linear cookbook approach to patient care.
So, where to from here?

“Paramedics displayed the ability to problem solve, critically analyse, perform complex reasoning and work cohesively with the patient as well as in a group. They were adept at rapidly forming clinical impressions in the critically ill with minimal information, and were able to modulate their interventions accordingly, while simultaneously continuing to gather data as they performed life-saving measures. Experienced paramedics are seen to gather, process and utilise information differently to the new graduate, portraying an interconnectedness of conscious and sub-conscious processing drawing on information from multiple sources culminating from both professional and personal experiences.”

Paramedic judgement, decision-making and cognitive processing: a review of the literature Australasian Journal of Paramedicine: 2019;16 Meriem Perona, Muhammad Aziz Rahman, Peter O’Meara BHA

The implications of this need to be reflected in our practice through ongoing mentoring, partnering the experienced with the novice, reflection and feedback post scene time, all which will go some way to encourage improvement in skills, competency and learning, which then translates into improved patient outcomes.
The LIFTMOR Randomised Controlled Trial

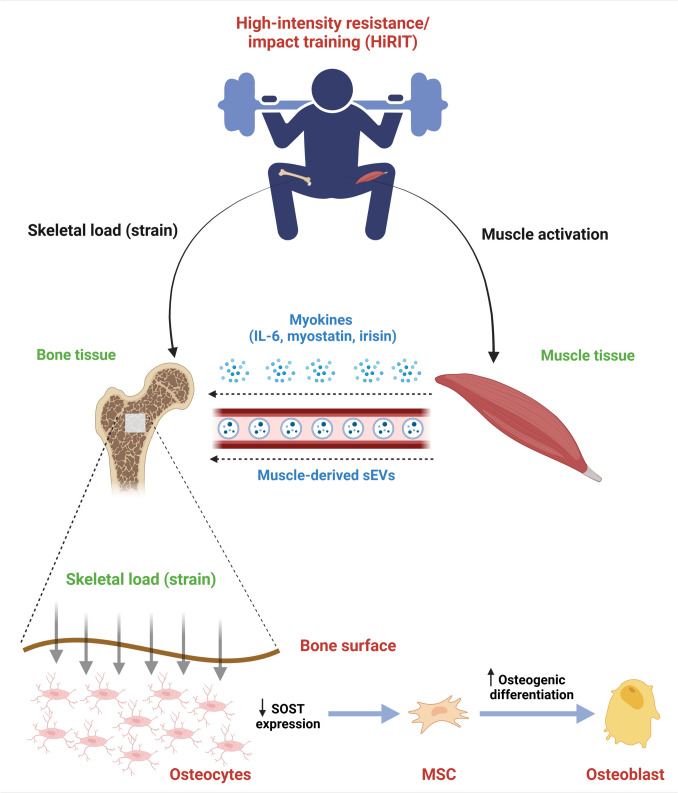
The LIFTMOR trial results are overwhelmingly good, delivering a groundbreaking shift in how medical professionals approach exercise for bone health. Published in the Journal of Bone and Mineral Research, the LIFTMOR Randomized Controlled Trial proved that high-intensity resistance and impact training (HiRIT) safely increases bone density in postmenopausal women and men with osteopenia or osteoporosis. Women with osteopenia or osteoporosis have traditionally been advised to exercise cautiously and avoid heavy lifting. LIFTMOR  challenges this approach, by asking an important question: Can postmenopausal women with low bone density safely lift heavy enough to stimulate stronger bones?

Core Study Design

LIFTMOR stands for Lifting Intervention for Training Muscle and Osteoporosis Rehabilitation. This randomized controlled trial included 101 postmenopausal women with an average age of 65. All had osteopenia or osteoporosis at the hip, spine, or both. The LIFTMOR trial was a high-quality research investigation of exercise for postmenopausal women with low bone mass.

  • Participants: 101 postmenopausal women with osteopenia or osteoporosis (average age 65).
  • Intervention: High-Intensity Resistance and Impact Training (HiRIT).
  • Comparison: A low-intensity home-based exercise control group.
  • Frequency: Twice weekly for 30 minutes, over an 8-month period.

Key Exercises Used

  • Barbell deadlifts
  • Back squats
  • Overhead military presses
  • Jumping chin-ups with drop landings (for impact loading) 

The Core Results

Prior to this trial, medical guidance typically restricted individuals with low bone density to gentle, low-impact movements out of fear of causing fractures. The trial compared an 8-month, twice-weekly program of heavy compound lifting (at 80–85% of 1-repetition maximum) against a low-intensity, home-based routine.

The findings dramatically favoured the heavy lifting group:

  • Functional Performance: Participants showed vast improvements in stature (height retention), back and leg strength, and functional balance metrics, which directly reduces fall risks.
  • Exceptional Safety: Under expert supervision, there were zero fractures and only one reported minor adverse event (a temporary lower back spasm) during the primary trial.

The Caveat: “Good” Comes With Strict Conditions

While the data itself is highly positive, physical therapists and bone health experts emphasize that the protocol is only “good” if executed under specific parameters:

  • Expert Supervision is Mandatory: The exercises utilized—barbell back squats, deadlifts, overhead presses, and jumping chin-ups with flat-footed landings—carry high structural risks if alignment is lost.
  • Prior Screening: The original trial rigorously screened participants to filter out severe comorbidities. Undertaking this exact protocol at home without an assessment or professional coaching introduces a high risk of vertebral compression fractures or joint strain.

The high-intensity program centred on four movements: the deadlift, back squat, overhead press, and a jumping chin-up with a drop landing.

After an initial period focused on learning proper technique, the three resistance exercises were performed for five sets of five repetitions at greater than 80–85% of one-repetition maximum. In practical terms, these were genuinely heavy loads—not light weights performed for many repetitions.

What did the researchers find?

  • Bone Density: The HiRIT group gained roughly 3% to 4% in lumbar spine bone mineral density and about 2% in the femoral neck (hip), whereas the control group continued to lose bone density.
  • Physical Function: Marked improvements occurred in functional performance, dynamic balance, and muscular strength (gains of 25–35%).
  • Safety: The high-intensity regimen was well-tolerated with high compliance and virtually no serious adverse events under professional supervision.

After eight months, lumbar-spine bone mineral density increased by approximately 2.9% in the high-intensity group. In contrast, the low-intensity group lost about 1.2%.

At the femoral neck, bone density was essentially maintained in the high-intensity group, increasing by approximately 0.3%, while the control group lost approximately 1.9%. Preventing the expected decline at the hip may itself be an important benefit.

The high-intensity group also demonstrated favourable changes in femoral-neck cortical thickness. Cortical bone forms the strong outer shell of bone and contributes substantially to the hip’s ability to tolerate loading.

More than stronger bones

LIFTMOR also produced substantial improvements in physical function. Leg and back-extensor strength increased by approximately 35–36%, and participants improved their sit-to-stand ability, functional reach, mobility, and vertical-jump performance.

This matters because fracture risk is influenced by more than bone density. Strength, balance, mobility, and the ability to recover from a misstep can all affect the likelihood of falling—and whether a fall results in injury.

The Bottom Line

The LIFTMOR trial helped overturn the assumption that women with low bone density should train only with light weights. Its message is not simply “lift heavy.”

With appropriate screening, progressive loading, excellent technique, and qualified supervision, postmenopausal women can train at high intensity—and may meaningfully improve bone density, strength, and physical function. For more info or one to one consults please reach out ..

References:

https://pubmed.ncbi.nlm.nih.gov/28975661

https://pubmed.ncbi.nlm.nih.gov/30861219

https://pubmed.ncbi.nlm.nih.gov/29125144

https://pubmed.ncbi.nlm.nih.gov/36310762